
Tue, Sep 15, 2026
[Archive]
Volume 2, Issue 2 (IJHMD 2025)
IJHMD 2025, 2(2): 7-12 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Emrani N, Izad F, Rajabi A, Shahryari A. Assessment of infection prevention and control programs in dental clinics of dentistry school: A cross-sectional study. IJHMD 2025; 2 (2) :7-12
URL: http://jhd.goums.ac.ir/article-1-42-en.html
URL: http://jhd.goums.ac.ir/article-1-42-en.html


1- Department of Pediatric Dentistry, Faculty of Dentistry, Golestan University of Medical Sciences, Gorgan, Iran
2- Student Research Committee, School of Dentistry, Golestan University of Medical Sciences, Gorgan, Iran
3- Department of Biostatistics and Epidemiology, Faculty of Health, Golestan University of Medical Sciences, Gogan, Iran; Environmental Health Research Center, Golestan University of Medical Sciences, Gogan, Iran
4- Environmental Health Research Center, Golestan University of Medical Sciences, Gogan, Iran; Department of Environmental Health Engineering, Faculty of Health, Golestan University of Medical Sciences, Gorgan, Iran ,Dr.shahryari@goums.ac.ir
2- Student Research Committee, School of Dentistry, Golestan University of Medical Sciences, Gorgan, Iran
3- Department of Biostatistics and Epidemiology, Faculty of Health, Golestan University of Medical Sciences, Gogan, Iran; Environmental Health Research Center, Golestan University of Medical Sciences, Gogan, Iran
4- Environmental Health Research Center, Golestan University of Medical Sciences, Gogan, Iran; Department of Environmental Health Engineering, Faculty of Health, Golestan University of Medical Sciences, Gorgan, Iran ,
Full-Text [PDF 491 kb]
(598 Downloads)
| Abstract (HTML) (2214 Views)
Discussion
Transmission of dental infections is a significant public health concern in dental clinics (33). The IPAC program was implemented to mitigate the risk of infection transmission, which can occur through blood, saliva, contaminated air droplets, and unsterilized instruments (34). The IPAC program was primarily implemented in accordance with the US CDC guidelines, as outlined in the sections on policies and practices, as well as through direct observation of personnel and patient-care practices (Tables 1 and 2). The written infection prevention policies and procedures were developed in accordance with IPAC regulations. In the present research, trained individuals were assigned responsibility for coordinating the infection prevention program across additional departments.
PPE was available for dentistry professionals and dental workers; however, defective implementation of PPE was reported by some service workers (Table 1: I.6, and Table 2: II.2). The statistical analysis showed no significant difference between all service workers in different wards of the dentistry school (p>0.05). Interviews suggested that this may be attributed to a lack of biosafety awareness or oversimplification, which could have overlooked certain relevant complexities of oral diseases. Biosafety training courses can help workers enhance their knowledge about the risks of infection transmission, most notably, blood-borne infections caused by sharp objects and needles during percutaneous injuries (27). According to the U.S. Occupational Safety and Health Administration (OSHA), the risk of sharp object injuries can be reduced by up to 88% by implementing standard processes (35). Implementing a rapid and early detection system is crucial for identifying potential infections at their initial stages, thereby minimizing the risk of cross-infection among dental healthcare personnel, students, and patients during treatment procedures (36).
In this study, respiratory hygiene and cough etiquette did not meet the infection control requirements in all departments. Similar results have also been reported regarding the incorrect use of face masks in a study conducted by Haghani et al. (37). The CDC recommends that patients with respiratory symptoms should not be admitted to the entrance of the dental clinic (14). Although it is challenging to prevent patients with respiratory symptoms from receiving dental treatment during the disease in developing countries, it is essential to raise awareness about the use of masks to enhance safe working environment practices and prevent respiratory problems. A significant hygiene issue exists in university dental clinics, primarily due to the provision of more affordable services compared to private dental clinics, which results in overcrowding. Additionally, people who work at these clinics are commonly from the middle class of society, in terms of education, income, occupation, or social status. Hence, designing a standard IPAC program and implementing continuous monitoring is crucial to minimizing the spread of infectious agents (38).
The study's results demonstrated that the safety requirements for dental healthcare personnel were not satisfactory in all departments. For example, there was no document about the medical examination of healthcare for all workers from the time of recruitment to the time of the study. Moreover, there was no recorded vaccination for all staff, particularly service workers. Haridi et al. have previously reported a low coverage of hepatitis B vaccination among dental personnel in Saudi Arabia (39). Immunizing DHCP is necessary due to the hazardous health risks associated with diseases, such as hepatitis B, in dental clinics (14).
In the present study, hand washing was performed correctly with soap and water by most of the staff. Some service workers did not wash their hands after attending to each patient. Their justification was that they were using latex gloves, which could protect their hands during daily work. This finding is consistent with a study conducted by John et al., who reported that 18% of healthcare personnel believed that there was no need for hand hygiene if gloves were used (40). It appears that additional training is necessary for these workers to increase awareness about the potential hazards of biological agents to which they are exposed. Research by Saveanu et al. also confirmed a significant gap in IPAC knowledge and the need for sustained continuing medical education (41).
The result demonstrates that safe injection practices were acceptable; however, there was a slight problem in some wards regarding the aseptic technique. Due to the biohazardous risks to human health, education on environmental cleaning and the proper collection of biological dental waste is critical at the end of each working day (42). In the present work, disinfection and sterilization of instruments, equipment, and environment failed in some departments (I.9 and I.10 in Table 1, and II.5 and II.6 of Table 2). Notably, there were few documents about the result of biological indicator tests to reveal an accurate process without any mistakes in disinfection and sterilization (39). According to the American Dental Association Guidelines, critical dental instruments, such as extraction forceps and scalpel blades, that penetrate soft tissue or bone should be sterilized after each use. Other instruments, such as amalgam condensers, also known as semi-critical, are recommended to be sterilized after each use due to their contact with oral tissues (43). The use of automatic equipment is recommended to enhance cleaning efficiency and minimize exposure to biological agents. Moreover, service department employees are required to use PPE.
Results showed that a written plan existed for sampling and microbial analysis of the water. The dental chair features a complex network of water lines and tubes to supply water for instruments, such as turbine handpieces and air and water syringes, during dental treatment (20). There is some research related to the contamination of dental water by heterotrophic bacteria, due to biofilm formation in DUWLs as a result of low flow and prolonged stagnation periods, and also suction back from the patient's mouth into DUWLs (44). Accordingly, having a continuous monitoring program is essential to minimize the risk of infection through DUWLs.
Strengths and limitations
The result provides information about the IPAC program in a dentistry school in a daily work routine. Hence, this finding is valuable for analyzing the problem and then implementing corrective actions to improve the safety of DWEs. However, it is essential to acknowledge the limitations of this study in its analysis and interpretation. The results obtained from small dental schools may not apply to all dental schools within medical science universities. Future research should aim to address these limitations by conducting multi-center studies with larger sample sizes to ensure the strength of the data collected. Additionally, efforts should be made to enhance the statistical power of analyses to provide more reliable results for improvement of the IPAC programs.
Conclusion
The findings indicated that the infection control program was satisfactory. However, not meeting all criteria could have profound implications for patient safety and well-being. Therefore, regular inspections to assess the implementation of infection control procedures are crucial in providing a safe workplace for dental professionals in dental clinics. Furthermore, greater emphasis should be placed on training courses, infection prevention, and control programs in dental clinics.
Acknowledgement
We would like to express our gratitude to Golestan University of Medical Sciences and the Vice-Chancellor of Research and Technology for their financial support in conducting this study. We also extend our appreciation to the dentists and dental healthcare workers for their participation.
Funding sources
This research has been funded by Golestan University of Medical Sciences (Grant No. 113463).
Ethical statement
The current research is based on a dissertation project. All procedures adhered to the ethical principles established by the regional research committee. The protocol for this study was approved by the ethical committee at Golestan University of Medical Sciences, with the registration code IR.GOUMS.REC.1402.319.
Conflicts of interest
The authors declare that they have no competing interests.
Author contributions
A.S.: Conceptualization, Supervision, Writing, Review, and Editing. N.E.: Funding acquisition, Supervision, Writing, Review, and Editing. F.I.: Collection of data, Writing, and Review. AR: Methodology, Analysis of the data, Review, and Editing. All authors contributed to the preparation of the manuscript and agreed to the published version.
Data availability statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Full-Text: (42 Views)
Introduction
Healthcare-associated infections (HAIs) pose a significant challenge for healthcare systems worldwide, resulting in substantial costs for both individuals and governments (1,2). A primary concern in this regard is the significant role of HAIs to morbidity and mortality rates in healthcare facilities, an issue particularly common in high-income countries (3). For instance, in European countries, which boast comprehensive healthcare services, over 2.5 million new HAI cases are reported annually (4). According to World Health Organization (WHO) estimates, the prevalence of HAIs is approximately 5-15% in high-income countries and is estimated as high as 25% in lower-middle-income countries (5). Therefore, the WHO emphasizes the critical importance of implementing infection prevention and control (IPAC) programs to minimize the risk of HAIs for both patients and healthcare workers (6,7).
In recent years, HAIs have been prioritized as a critical public health issue due to their substantial financial burden on healthcare systems (8). This heightened focus is also driven by the rising rates of morbidity and mortality among vulnerable populations, particularly individuals with immune system disorders (9). Common causative agents of HAIs include methicillin-resistant Staphylococcus aureus (MRSA), Pseudomonas aeruginosa, other non-pseudomonas Gram-negative bacteria (Such as E. coli and Klebsiella sp.), Salmonella sp., Shigella sp., Staphylococcus aureus, and Clostridium difficile (10,11). Many of these pathogens demonstrate significant environmental resistance, capable of surviving on surfaces for several days to months. This can lead to transmission, especially when IPAC precautions are not rigorously followed in healthcare settings (12,13).
In 2003, the US Centers for Disease Control and Prevention (CDC) established a guideline for IPAC in dental healthcare settings to promote and ensure the adoption of appropriate infection prevention policies and practices (14). This guideline outlines critical elements, including comprehensive training of dental healthcare personnel (DHCP) in infection prevention, the provision of safe patient care, and the maintenance of a safe working environment (15). The DHCP team includes dentists, dental hygienists, dental assistants, and dental laboratory technicians, all working within the Dental Work Environment (DWE). Due to their close contact with patients and potential exposure to infectious agents, all members of the DHCP are at high risk of acquiring occupational infections during dental procedures (16,17).
In DWEs, pathogens are transmitted through three main routes: direct contact with blood or oral fluids, indirect contact with contaminated instruments or surfaces, and inhalation of airborne microorganisms generated by patients or devices, such as handpieces (18,19). Common pathogens include the hepatitis B and C viruses, HIV, SARS-CoV-2, and Pseudomonas aeruginosa (20-23). Dentists face a significantly high risk of HBV infection-estimated at ten times the general population’s risk-primarily through percutaneous injuries via contaminated instruments (24). Pathogens can survive in saliva, blood, inadequately disinfected equipment, and in untreated dental unit waterlines (19,25). Despite these risks, studies indicate that dental students and practitioners in some regions have insufficient knowledge of infection control (26-28), and many dentists express concern about occupational infections (29). Therefore, strict adherence to evidence-based IPAC programs is paramount to mitigating transmission risks in dental clinics (30,31).
This study was conducted to evaluate the adherence to IPAC policies at a university dental clinic and provide recommendations for preventing infectious diseases and addressing personnel health and safety concerns in accordance with IPAC protocols.
Methods
This cross-sectional study, conducted at the School of Dentistry, Golestan University of Medical Sciences (Located in Gorgan, northern Iran) from November 2023 to February 2024, focused on assessing the infection prevention and control (IPAC) program in dental clinics. The dental clinics comprised 10 departments: orthodontics, endodontics, restorative dentistry, pediatric dentistry, surgical dentistry, prosthetic dentistry, periodontics, oral medicine, pathology, and radiology. The pathology and radiology wards were excluded from the study because these two departments were not operating and did not accept patients during the research period.
Data was collected using the infection prevention checklist provided by the US CDC for dental clinics. The original checklist included two main sections. The first part consisted of 59 questions organized into various categories, including administrative measures, infection prevention education and training, safety for dental health care personnel, program evaluation, hand hygiene, personal protective equipment (PPE), respiratory hygiene and cough etiquette, sharps safety, safe injection practices, sterilization and disinfection of patient-care items and devices, environmental infection prevention and control, and dental unit water quality. The second part of the questionnaire consisted of eight sections, totaling 69 questions, which aimed to observe personnel and patient-care practices directly. This section covered several important topics, including hand hygiene, the proper use of personal protective equipment (PPE), respiratory hygiene and cough etiquette, sharps safety, safe injection practices, sterilization and disinfection of patient care items and devices, environmental infection prevention and control, and the quality of dental unit water. The responses to these questions were organized in a closed-ended format, with yes or no answer choices (14).
The checklist underwent a comprehensive review and assessment by a panel of experts in dentistry, epidemiology, and environmental health, specifically focused on the feasibility of establishing a dental school in Gorgan. To ensure the accuracy and relevance of responses, the checklist was meticulously surveyed by a dedicated team comprising faculty members from the dentistry school and associated researchers. The content validity index (CVI) and content validity ratio (CVR) were calculated and found to be above the acceptable threshold of 0.84. Reliability was assessed through inter-rater evaluation on a pilot sample, showing a high Cohen's kappa coefficient of 0.81.
Data collection was facilitated through direct observations of dental wards, complemented by interviews with the department supervisor, which provided valuable insights into the prevailing environmental conditions. This multifaceted approach ensured a thorough evaluation of the proposed dentistry program's institutional readiness and potential impact (32). Following the research contract, the percentile was used for statistical analysis, in which a given percentage of data points falls into acceptable, average, or unacceptable categories. For example, a score of 75% indicates an adequate and satisfactory performance of the subjects in each section. Scores falling between 50% and 75% indicate an average status, while scores below 50% signify a poor and unacceptable situation within the department. Data coding was performed by the research team after data collection.
The data were statistically processed using SPSS version 22 (IBM, USA) to summarize them in terms of frequencies and percentages. The chi-square test (χ2) was employed to ascertain the relationship between variables across various departments, with a P-value of less than 0.05 considered statistically significant.
Results
The results of this study showed that 82% of the criteria related to the IPAC program followed the US CDC guide. In policies and practices (First part), the highest and lowest scores were related to hand hygiene and the safety of dental healthcare personnel. In addition, environmental infection control and respiratory hygiene and cough etiquette received the highest and lowest scores, respectively, from the section on direct observation of personnel and patient-care practices. In terms of the IPAC program score, sections I. 1 to I.12 relate to the Policies and Practices data, and sections II.1 to II.8 relate to the Direct Observation of Personnel and Patient-Care Practices, as shown in Figure 1.
The results of the parameter measurements showed that these variables did not exhibit any tangible changes across different wards. The results indicate significant differences in the implementation of IPAC program items, specifically in the areas of respiratory hygiene and cough etiquette (I.7), sharps safety (I.8), sterilization and disinfection of patient care items and devices (I.10), hand hygiene (II.1), sharps safety (II.4), safe injection practices (II.5), sterilization and disinfection of patient care items and device (II.6), environmental infection prevention and control (II.7), and dental unit water quality (II.8), across different dental clinic wards. The scores (%) of the IPAC program, regarding policies and practices, as well as direct observations of personnel and patient care practices, are presented separately for each ward of the dental clinics in Tables 1 and 2.
Healthcare-associated infections (HAIs) pose a significant challenge for healthcare systems worldwide, resulting in substantial costs for both individuals and governments (1,2). A primary concern in this regard is the significant role of HAIs to morbidity and mortality rates in healthcare facilities, an issue particularly common in high-income countries (3). For instance, in European countries, which boast comprehensive healthcare services, over 2.5 million new HAI cases are reported annually (4). According to World Health Organization (WHO) estimates, the prevalence of HAIs is approximately 5-15% in high-income countries and is estimated as high as 25% in lower-middle-income countries (5). Therefore, the WHO emphasizes the critical importance of implementing infection prevention and control (IPAC) programs to minimize the risk of HAIs for both patients and healthcare workers (6,7).
In recent years, HAIs have been prioritized as a critical public health issue due to their substantial financial burden on healthcare systems (8). This heightened focus is also driven by the rising rates of morbidity and mortality among vulnerable populations, particularly individuals with immune system disorders (9). Common causative agents of HAIs include methicillin-resistant Staphylococcus aureus (MRSA), Pseudomonas aeruginosa, other non-pseudomonas Gram-negative bacteria (Such as E. coli and Klebsiella sp.), Salmonella sp., Shigella sp., Staphylococcus aureus, and Clostridium difficile (10,11). Many of these pathogens demonstrate significant environmental resistance, capable of surviving on surfaces for several days to months. This can lead to transmission, especially when IPAC precautions are not rigorously followed in healthcare settings (12,13).
In 2003, the US Centers for Disease Control and Prevention (CDC) established a guideline for IPAC in dental healthcare settings to promote and ensure the adoption of appropriate infection prevention policies and practices (14). This guideline outlines critical elements, including comprehensive training of dental healthcare personnel (DHCP) in infection prevention, the provision of safe patient care, and the maintenance of a safe working environment (15). The DHCP team includes dentists, dental hygienists, dental assistants, and dental laboratory technicians, all working within the Dental Work Environment (DWE). Due to their close contact with patients and potential exposure to infectious agents, all members of the DHCP are at high risk of acquiring occupational infections during dental procedures (16,17).
In DWEs, pathogens are transmitted through three main routes: direct contact with blood or oral fluids, indirect contact with contaminated instruments or surfaces, and inhalation of airborne microorganisms generated by patients or devices, such as handpieces (18,19). Common pathogens include the hepatitis B and C viruses, HIV, SARS-CoV-2, and Pseudomonas aeruginosa (20-23). Dentists face a significantly high risk of HBV infection-estimated at ten times the general population’s risk-primarily through percutaneous injuries via contaminated instruments (24). Pathogens can survive in saliva, blood, inadequately disinfected equipment, and in untreated dental unit waterlines (19,25). Despite these risks, studies indicate that dental students and practitioners in some regions have insufficient knowledge of infection control (26-28), and many dentists express concern about occupational infections (29). Therefore, strict adherence to evidence-based IPAC programs is paramount to mitigating transmission risks in dental clinics (30,31).
This study was conducted to evaluate the adherence to IPAC policies at a university dental clinic and provide recommendations for preventing infectious diseases and addressing personnel health and safety concerns in accordance with IPAC protocols.
Methods
This cross-sectional study, conducted at the School of Dentistry, Golestan University of Medical Sciences (Located in Gorgan, northern Iran) from November 2023 to February 2024, focused on assessing the infection prevention and control (IPAC) program in dental clinics. The dental clinics comprised 10 departments: orthodontics, endodontics, restorative dentistry, pediatric dentistry, surgical dentistry, prosthetic dentistry, periodontics, oral medicine, pathology, and radiology. The pathology and radiology wards were excluded from the study because these two departments were not operating and did not accept patients during the research period.
Data was collected using the infection prevention checklist provided by the US CDC for dental clinics. The original checklist included two main sections. The first part consisted of 59 questions organized into various categories, including administrative measures, infection prevention education and training, safety for dental health care personnel, program evaluation, hand hygiene, personal protective equipment (PPE), respiratory hygiene and cough etiquette, sharps safety, safe injection practices, sterilization and disinfection of patient-care items and devices, environmental infection prevention and control, and dental unit water quality. The second part of the questionnaire consisted of eight sections, totaling 69 questions, which aimed to observe personnel and patient-care practices directly. This section covered several important topics, including hand hygiene, the proper use of personal protective equipment (PPE), respiratory hygiene and cough etiquette, sharps safety, safe injection practices, sterilization and disinfection of patient care items and devices, environmental infection prevention and control, and the quality of dental unit water. The responses to these questions were organized in a closed-ended format, with yes or no answer choices (14).
The checklist underwent a comprehensive review and assessment by a panel of experts in dentistry, epidemiology, and environmental health, specifically focused on the feasibility of establishing a dental school in Gorgan. To ensure the accuracy and relevance of responses, the checklist was meticulously surveyed by a dedicated team comprising faculty members from the dentistry school and associated researchers. The content validity index (CVI) and content validity ratio (CVR) were calculated and found to be above the acceptable threshold of 0.84. Reliability was assessed through inter-rater evaluation on a pilot sample, showing a high Cohen's kappa coefficient of 0.81.
Data collection was facilitated through direct observations of dental wards, complemented by interviews with the department supervisor, which provided valuable insights into the prevailing environmental conditions. This multifaceted approach ensured a thorough evaluation of the proposed dentistry program's institutional readiness and potential impact (32). Following the research contract, the percentile was used for statistical analysis, in which a given percentage of data points falls into acceptable, average, or unacceptable categories. For example, a score of 75% indicates an adequate and satisfactory performance of the subjects in each section. Scores falling between 50% and 75% indicate an average status, while scores below 50% signify a poor and unacceptable situation within the department. Data coding was performed by the research team after data collection.
The data were statistically processed using SPSS version 22 (IBM, USA) to summarize them in terms of frequencies and percentages. The chi-square test (χ2) was employed to ascertain the relationship between variables across various departments, with a P-value of less than 0.05 considered statistically significant.
Results
The results of this study showed that 82% of the criteria related to the IPAC program followed the US CDC guide. In policies and practices (First part), the highest and lowest scores were related to hand hygiene and the safety of dental healthcare personnel. In addition, environmental infection control and respiratory hygiene and cough etiquette received the highest and lowest scores, respectively, from the section on direct observation of personnel and patient-care practices. In terms of the IPAC program score, sections I. 1 to I.12 relate to the Policies and Practices data, and sections II.1 to II.8 relate to the Direct Observation of Personnel and Patient-Care Practices, as shown in Figure 1.
The results of the parameter measurements showed that these variables did not exhibit any tangible changes across different wards. The results indicate significant differences in the implementation of IPAC program items, specifically in the areas of respiratory hygiene and cough etiquette (I.7), sharps safety (I.8), sterilization and disinfection of patient care items and devices (I.10), hand hygiene (II.1), sharps safety (II.4), safe injection practices (II.5), sterilization and disinfection of patient care items and device (II.6), environmental infection prevention and control (II.7), and dental unit water quality (II.8), across different dental clinic wards. The scores (%) of the IPAC program, regarding policies and practices, as well as direct observations of personnel and patient care practices, are presented separately for each ward of the dental clinics in Tables 1 and 2.
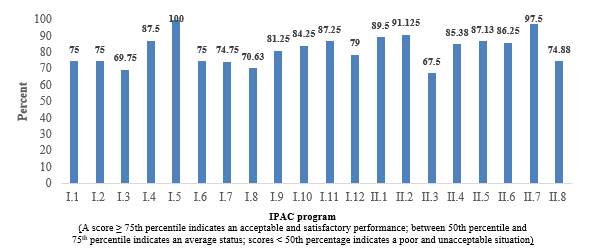 Figure 1. The scores of the IPAC program are categorized as follows: I.1 to I.12 relate to policy and practice data, and II.1 to II.8 relate to direct observation of personnel and patient care practices. I.1 Administrative measures, I.2 Infection prevention education and training, I.3 Dental health care personnel safety, I.4 Program evaluation, I.5 Hand hygiene, I.6 Personal protective equipment, I.7 Respiratory hygiene and cough etiquette, I.8 Sharps safety, I.9 Safe injection practices, I.10 Sterilization and disinfection of patient care items and devices, I.11 Environmental infection prevention and control, I.12 Dental unit water quality. II.1 Hand hygiene is performed correctly, II.2 Personal protective equipment is used correctly, II.3 Respiratory hygiene and cough etiquette, II.4 Sharps safety, II.5 Safe injection practices, II.6 Sterilization and disinfection of patient-care Items and devices, II.7 Environmental infection prevention and control, and II.8 Dental unit water quality |
|
Table 1. Obtaining score (%) of IPAC program related to the policies and practices data separately for each ward of dental clinics (A score ≥ 75th percentile indicates an acceptable and satisfactory performance; between 50th percentile and 75th percentile indicates an average status; scores < 50th percentile indicate a poor and unacceptable situation)
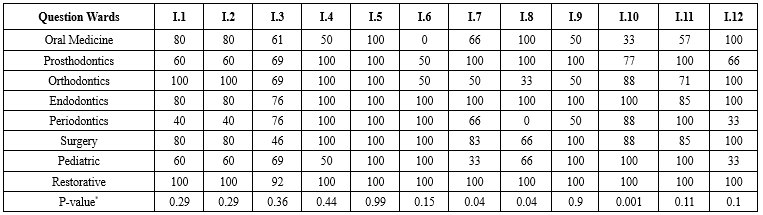 I.1 Administrative measures, I.2 Infection prevention education and training, I.3 Dental health care personnel safety, I.4 Program evaluation, I.5 Hand hygiene, I.6 Personal protective equipment, I.7 Respiratory hygiene and cough etiquette, I.8 Sharps safety, I.9 Safe injection practices, I.10 Sterilization and disinfection of patient care items and devices, I.11 Environmental infection prevention and control, I.12 Dental unit water quality *Chi-square test Table 2. Obtaining score (%) of IPAC program related to the direct observation of personnel and patient care practices separately for each ward of dental clinics (A score ≥ 75th percentile indicates an acceptable and satisfactory performance; between 50th percentile and 75th percentile indicates an average status; scores < 50th percentile indicate a poor and unacceptable situation) 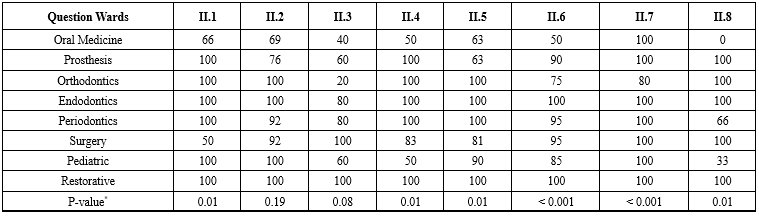 II.1 Hand hygiene is performed correctly, II.2 Personal protective equipment is used correctly, II.3 Respiratory hygiene and cough etiquette, II.4 Sharps safety, II.5 Safe injection practices, II.6 Sterilization and disinfection of patient care items and devices, II.7 Environmental infection prevention and control, and II.8 Dental unit water quality *Chi-square test |
Discussion
Transmission of dental infections is a significant public health concern in dental clinics (33). The IPAC program was implemented to mitigate the risk of infection transmission, which can occur through blood, saliva, contaminated air droplets, and unsterilized instruments (34). The IPAC program was primarily implemented in accordance with the US CDC guidelines, as outlined in the sections on policies and practices, as well as through direct observation of personnel and patient-care practices (Tables 1 and 2). The written infection prevention policies and procedures were developed in accordance with IPAC regulations. In the present research, trained individuals were assigned responsibility for coordinating the infection prevention program across additional departments.
PPE was available for dentistry professionals and dental workers; however, defective implementation of PPE was reported by some service workers (Table 1: I.6, and Table 2: II.2). The statistical analysis showed no significant difference between all service workers in different wards of the dentistry school (p>0.05). Interviews suggested that this may be attributed to a lack of biosafety awareness or oversimplification, which could have overlooked certain relevant complexities of oral diseases. Biosafety training courses can help workers enhance their knowledge about the risks of infection transmission, most notably, blood-borne infections caused by sharp objects and needles during percutaneous injuries (27). According to the U.S. Occupational Safety and Health Administration (OSHA), the risk of sharp object injuries can be reduced by up to 88% by implementing standard processes (35). Implementing a rapid and early detection system is crucial for identifying potential infections at their initial stages, thereby minimizing the risk of cross-infection among dental healthcare personnel, students, and patients during treatment procedures (36).
In this study, respiratory hygiene and cough etiquette did not meet the infection control requirements in all departments. Similar results have also been reported regarding the incorrect use of face masks in a study conducted by Haghani et al. (37). The CDC recommends that patients with respiratory symptoms should not be admitted to the entrance of the dental clinic (14). Although it is challenging to prevent patients with respiratory symptoms from receiving dental treatment during the disease in developing countries, it is essential to raise awareness about the use of masks to enhance safe working environment practices and prevent respiratory problems. A significant hygiene issue exists in university dental clinics, primarily due to the provision of more affordable services compared to private dental clinics, which results in overcrowding. Additionally, people who work at these clinics are commonly from the middle class of society, in terms of education, income, occupation, or social status. Hence, designing a standard IPAC program and implementing continuous monitoring is crucial to minimizing the spread of infectious agents (38).
The study's results demonstrated that the safety requirements for dental healthcare personnel were not satisfactory in all departments. For example, there was no document about the medical examination of healthcare for all workers from the time of recruitment to the time of the study. Moreover, there was no recorded vaccination for all staff, particularly service workers. Haridi et al. have previously reported a low coverage of hepatitis B vaccination among dental personnel in Saudi Arabia (39). Immunizing DHCP is necessary due to the hazardous health risks associated with diseases, such as hepatitis B, in dental clinics (14).
In the present study, hand washing was performed correctly with soap and water by most of the staff. Some service workers did not wash their hands after attending to each patient. Their justification was that they were using latex gloves, which could protect their hands during daily work. This finding is consistent with a study conducted by John et al., who reported that 18% of healthcare personnel believed that there was no need for hand hygiene if gloves were used (40). It appears that additional training is necessary for these workers to increase awareness about the potential hazards of biological agents to which they are exposed. Research by Saveanu et al. also confirmed a significant gap in IPAC knowledge and the need for sustained continuing medical education (41).
The result demonstrates that safe injection practices were acceptable; however, there was a slight problem in some wards regarding the aseptic technique. Due to the biohazardous risks to human health, education on environmental cleaning and the proper collection of biological dental waste is critical at the end of each working day (42). In the present work, disinfection and sterilization of instruments, equipment, and environment failed in some departments (I.9 and I.10 in Table 1, and II.5 and II.6 of Table 2). Notably, there were few documents about the result of biological indicator tests to reveal an accurate process without any mistakes in disinfection and sterilization (39). According to the American Dental Association Guidelines, critical dental instruments, such as extraction forceps and scalpel blades, that penetrate soft tissue or bone should be sterilized after each use. Other instruments, such as amalgam condensers, also known as semi-critical, are recommended to be sterilized after each use due to their contact with oral tissues (43). The use of automatic equipment is recommended to enhance cleaning efficiency and minimize exposure to biological agents. Moreover, service department employees are required to use PPE.
Results showed that a written plan existed for sampling and microbial analysis of the water. The dental chair features a complex network of water lines and tubes to supply water for instruments, such as turbine handpieces and air and water syringes, during dental treatment (20). There is some research related to the contamination of dental water by heterotrophic bacteria, due to biofilm formation in DUWLs as a result of low flow and prolonged stagnation periods, and also suction back from the patient's mouth into DUWLs (44). Accordingly, having a continuous monitoring program is essential to minimize the risk of infection through DUWLs.
Strengths and limitations
The result provides information about the IPAC program in a dentistry school in a daily work routine. Hence, this finding is valuable for analyzing the problem and then implementing corrective actions to improve the safety of DWEs. However, it is essential to acknowledge the limitations of this study in its analysis and interpretation. The results obtained from small dental schools may not apply to all dental schools within medical science universities. Future research should aim to address these limitations by conducting multi-center studies with larger sample sizes to ensure the strength of the data collected. Additionally, efforts should be made to enhance the statistical power of analyses to provide more reliable results for improvement of the IPAC programs.
Conclusion
The findings indicated that the infection control program was satisfactory. However, not meeting all criteria could have profound implications for patient safety and well-being. Therefore, regular inspections to assess the implementation of infection control procedures are crucial in providing a safe workplace for dental professionals in dental clinics. Furthermore, greater emphasis should be placed on training courses, infection prevention, and control programs in dental clinics.
Acknowledgement
We would like to express our gratitude to Golestan University of Medical Sciences and the Vice-Chancellor of Research and Technology for their financial support in conducting this study. We also extend our appreciation to the dentists and dental healthcare workers for their participation.
Funding sources
This research has been funded by Golestan University of Medical Sciences (Grant No. 113463).
Ethical statement
The current research is based on a dissertation project. All procedures adhered to the ethical principles established by the regional research committee. The protocol for this study was approved by the ethical committee at Golestan University of Medical Sciences, with the registration code IR.GOUMS.REC.1402.319.
Conflicts of interest
The authors declare that they have no competing interests.
Author contributions
A.S.: Conceptualization, Supervision, Writing, Review, and Editing. N.E.: Funding acquisition, Supervision, Writing, Review, and Editing. F.I.: Collection of data, Writing, and Review. AR: Methodology, Analysis of the data, Review, and Editing. All authors contributed to the preparation of the manuscript and agreed to the published version.
Data availability statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Type of Study: Original Article |
Subject:
Public health
Received: 2024/12/15 | Accepted: 2025/09/29 | Published: 2026/09/5
Received: 2024/12/15 | Accepted: 2025/09/29 | Published: 2026/09/5
References
1. Saleem Z, Godman B, Hassali MA, Hashmi FK, Azhar F, Rehman IU. Point prevalence surveys of health-care-associated infections: a systematic review. Pathog Glob Health. 2019;113(4):191-205 [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Patil RK, Kabera B, Muia CK, Ale BM. Hospital acquired infections in a private paediatric hospital in Kenya: a retrospective cross-sectional study. Pan Afr Med J. 2022:41:28. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Haque M, McKimm J, Sartelli M, Dhingra S, Labricciosa FM, Islam S, et al. Strategies to prevent healthcare-associated infections: a narrative overview. Risk Manag Healthc Policy.2020 Sep:13:1765-1780. [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Cassini A, Plachouras D, Eckmanns T, Abu Sin M, Blank H-P, Ducomble T, et al. Burden of six healthcare-associated infections on European population health: estimating incidence-based disability-adjusted life years through a population prevalence-based modelling study. PLoS Med. 2016;13(10):e1002150 [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Raoofi S, Pashazadeh Kan F, Rafiei S, Hosseinipalangi Z, Noorani Mejareh Z, Khani S, et al. Global prevalence of nosocomial infection: A systematic review and meta-analysis. PloS one. 2023;18(1):e0274248. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Izadi N, Eshrati B, Etemad K, Mehrabi Y, Hashemi-Nazari S-S. Rate of the incidence of hospital-acquired infections in Iran based on the data of the national nosocomial infections surveillance. New Microbes New Infect. 2020;38:100768 [View at Publisher] [DOI] [PMID] [Google Scholar]
7. WHO. Core competencies for infection prevention and control professionals. Geneva: World Health Organization; 2020. [View at Publisher] [Google Scholar]
9. Kubde D, Badge AK, Ugemuge S, Shahu S. Importance of Hospital Infection Control. Cureus. 2023;15(12):e50931. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. World Health Organization. Overview of the IPC Situation Worldwide: Highlights of Achievements and Gaps 2022 [Internet]. Geneva: World Health Organization; 2022 [cited 2025 Oct 4]. Available from:https://www.who.int/publications/i/item/9789240051164. [View at Publisher]
11. Golfiroozi S, Fashayi F, Rajabi A, Shahryar A. Disinfectants efficacy in reducing pathogens related to health-care infection associated in universities hospitals of Gorgan, North of Iran. BMC Infect Dis. 2024;24(1):1113 [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Facciola A, Pellicano GF, Visalli G, Paolucci IA, Venanzi Rullo E, Ceccarelli M, et al. The role of the hospital environment in the healthcare-associated infections: a general review of the literature. European Review for Medical & Pharmacological Sciences. 2019;23(3). [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Dancer SJ, Kramer A. Four steps to clean hospitals: Look, Plan, Clea and Dry. J Hosp Infect. 2019;103(1):e1-e8 [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Kohn WG, Collins AS, Cleveland JL, Harte JA, Eklund KJ, Malvitz DM. Guidelines for infection control in dental health-care settings-2003. MMWR Recomm Rep. 2003;52(RR-17):1-61 [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Johnston C, Sunil V, Service D, Holt AM, Garber G, Macdonald L, et al. A public health response to a newly diagnosed case of hepatitis C associated with lapse in Infection Prevention and Control practices in a dental setting in Ontario, Canada. Can Commun Dis Rep. 2021;47(7-8):347-52. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Kalantari MH, Malekzadeh A, Emami A. The effect of disinfection with sodium hypochlorite 0.5% on dimensional stability of condensation silicone impression materials of speedex and irasil. J Dent (Shiraz). 2014;15(3):98-103. [View at Publisher] [PMID] [Google Scholar]
17. Shaghaghian S, Golkari A, Pardis S, Rezayi A. Occupational exposure of shiraz dental students to patients' blood and body fluid. J Dent (Shiraz). 2015;16(3):206-13. [View at Publisher] [PMID] [Google Scholar]
18. Milward MR, Cooper PR. Competency assessment for infection control in the undergraduate dental curriculum. Eur J Dent Educ. 2007;11(3):148-54. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Stomatol M. How to manage the Biological Risk in a Dental Clinic: Current and future perspectives. Revista Pubmed. 2017. [Google Scholar]
20. Bayani M, Raisolvaezin K, Almasi-Hashiani A, Mirhoseini SH. Bacterial biofilm prevalence in dental unit waterlines: a systematic review and meta-analysis. BMC Oral Health. 2023;23(1):158. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Spagnolo AM, Sartini M, Cristina ML. Microbial contamination of dental unit waterlines and potential risk of infection: a narrative review. Pathogens. 2020;9(8):651. [View at Publisher] [DOI] [PMID] [Google Scholar]
22. Amato A, Caggiano M, Amato M, Moccia G, Capunzo M, De Caro F. Infection control in dental practice during the COVID-19 pandemic. Int J Environ Res Public Health. 2020;17(13):4769. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Winning L, Lundy FT, Blackwood B, McAuley DF, El Karim I. Oral health care for the critically ill: a narrative review. Crit Care. 2021;25(1):353 [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Araujo MW, Andreana S. Risk and prevention of transmission of infectious diseases in dentistry. Quintessence Int. 2002;33(5):376-82. [View at Publisher] [PMID] [Google Scholar]
25. Bromberg N, Brizuela M. Preventing cross infection in the dental office. StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2023. [View at Publisher] [PMID] [Google Scholar]
26. Thomas MV, Jarboe G, Frazer RQ. Infection control in the dental office. Dent Clin North Am. 2008;52(3):609-28 [View at Publisher] [DOI] [PMID] [Google Scholar]
27. Denault D, Gardner H. OSHA bloodborne pathogen standards. USA: Treasure Island, FL, USA; 2021. [View at Publisher] [PMID] [Google Scholar]
28. El-Saaidi C, Dadras O, Musumari PM, Ono-Kihara M, Kihara M. Infection control knowledge, attitudes, and practices among students of public dental schools in Egypt. Int J Environ Res Public Health. 2021;18(12):6248. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Baudet A, Lizon J, Martrette J-M, Camelot F, Florentin A, Clément C. Dental unit waterlines: a survey of practices in Eastern France. Int J Environ Res Public Health. 2019;16(21):4242 [View at Publisher] [DOI] [PMID] [Google Scholar]
30. Sharma L, Pradhan D, Todkar M, Sinha K, Neha D. Infection control and dentistry: a review. Int j oral health med res. 2018;5(3):27-9. [View at Publisher] [DOI] [Google Scholar]
31. Ahmed NJ, Haseeb A, Elazab EM, Kheir HM, Hassali AA, Khan AH. Incidence of Healthcare-Associated Infections (HAIs) and the adherence to the HAIs' prevention strategies in a military hospital in Alkharj. Saudi Pharm J. 2021;29(10):1112-9 [View at Publisher] [DOI] [PMID] [Google Scholar]
32. Philip M. Questionnaire, Rating Scale and Checklist-how do they differ? Methods in Psychology. 2024;10:100145. [View at Publisher] [DOI] [Google Scholar]
33. Ibrahim NK, Alwafi HA, Sangoof SO, Turkistani AK, Alattas BM. Cross-infection and infection control in dentistry: Knowledge, attitude and practice of patients attended dental clinics in King Abdulaziz University Hospital, Jeddah, Saudi Arabia. J Infect Public Health. 2017;10(4):438-45 [View at Publisher] [DOI] [PMID] [Google Scholar]
34. Volgenant CM, Persoon IF, de Ruijter RA, de Soet J. Infection control in dental health care during and after the SARS‐CoV‐2 outbreak. Oral Dis. 2021;27(3):674-83. [View at Publisher] [DOI] [PMID] [Google Scholar]
35. Occupational Safety and Health Administration. Safety and Health Topics: Bloodborne Pathogens and Needlestick Prevention [Internet]. Washington, DC: U.S. Department of Labor, Occupational Safety and Health Administration; 2019 [cited 2025 Oct 4]. p. 43. Available from: https://www.osha.gov/bloodborne-pathogens. [View at Publisher] [Google Scholar]
36. Cicciù M. Water contamination risks at the dental clinic. Biology. 2020;9(3):43. [View at Publisher] [DOI] [PMID] [Google Scholar]
37. Haghani J, Ebrahimnejad H, Torabi-Parizi M, Karimi-Afshar M, Amiri R. Knowledge and Practice of Kerman Dentists about Infection Control in Digital Radiography. J Dent (Shiraz). 2022;23(4):467-71. [View at Publisher] [DOI] [PMID] [Google Scholar]
38. Zemouri C, de Soet H, Crielaard W, Laheij A. A scoping review on bio-aerosols in healthcare and the dental environment. PloS one. 2017;12(5):e0178007. [View at Publisher] [DOI] [PMID] [Google Scholar]
39. Haridi HK, Al-Ammar AS, Al-Mansour MI. Compliance with infection control standard precautions guidelines: a survey among dental healthcare workers in Hail Region, Saudi Arabia. Journal of infection prevention. 2016;17(6):268-76 [View at Publisher] [DOI] [PMID] [Google Scholar]
40. John A, Tomas ME, Cadnum JL, Mana TS, Jencson A, Shaikh A, et al. Are health care personnel trained in correct use of personal protective equipment? Am J Infect Control. 2016;44(7):840-2 [View at Publisher] [DOI] [PMID] [Google Scholar]
41. Saveanu CI, Dărăbăneanu G, Bobu LI, Anistoroaei D, Bamboi I, Ciortescu I, et al. A Cross-Sectional Questionnaire-Based Survey on Blood-Borne Infection Control among Romanian Dental Students. Medicina. 2022;58(9):1268. [View at Publisher] [DOI] [PMID] [Google Scholar]
42. Subramanian AK, Nivethigaa B, Srirengalakshmi M, Varghese RM, Navaneethan R, Babu H. Biomedical waste management practice in dentistry. Bioinformation. 2020;16(11):958-64. [View at Publisher] [DOI] [PMID] [Google Scholar]
43. Rutala WA, Weber DJ. Guideline for disinfection and sterilization in healthcare facilities, 2008. Update: 2019. [View at Publisher] [Google Scholar]
44. Fan C, Gu H, Liu L, Zhu H, Yan J, Huo Y. Distinct microbial community of accumulated biofilm in dental unit waterlines of different specialties. Front Cell Infect Microbiol. 2021;11:670211 [View at Publisher] [DOI] [PMID] [Google Scholar]
45. Błaszczyk B, Pajączkowska M, Nowicka J, Szymonowicz M, Zakrzewski W, Lubojański A, et al. Microbiological Evaluation of Water Used in Dental Units. Water. 2022;14(6):915. [View at Publisher] [DOI] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
